Lenvatinib Mesylate Targets VEGFR-2 and FGFR to Inhibit Hepatocellular Carcinoma Signaling
Copy code to add this image to your page
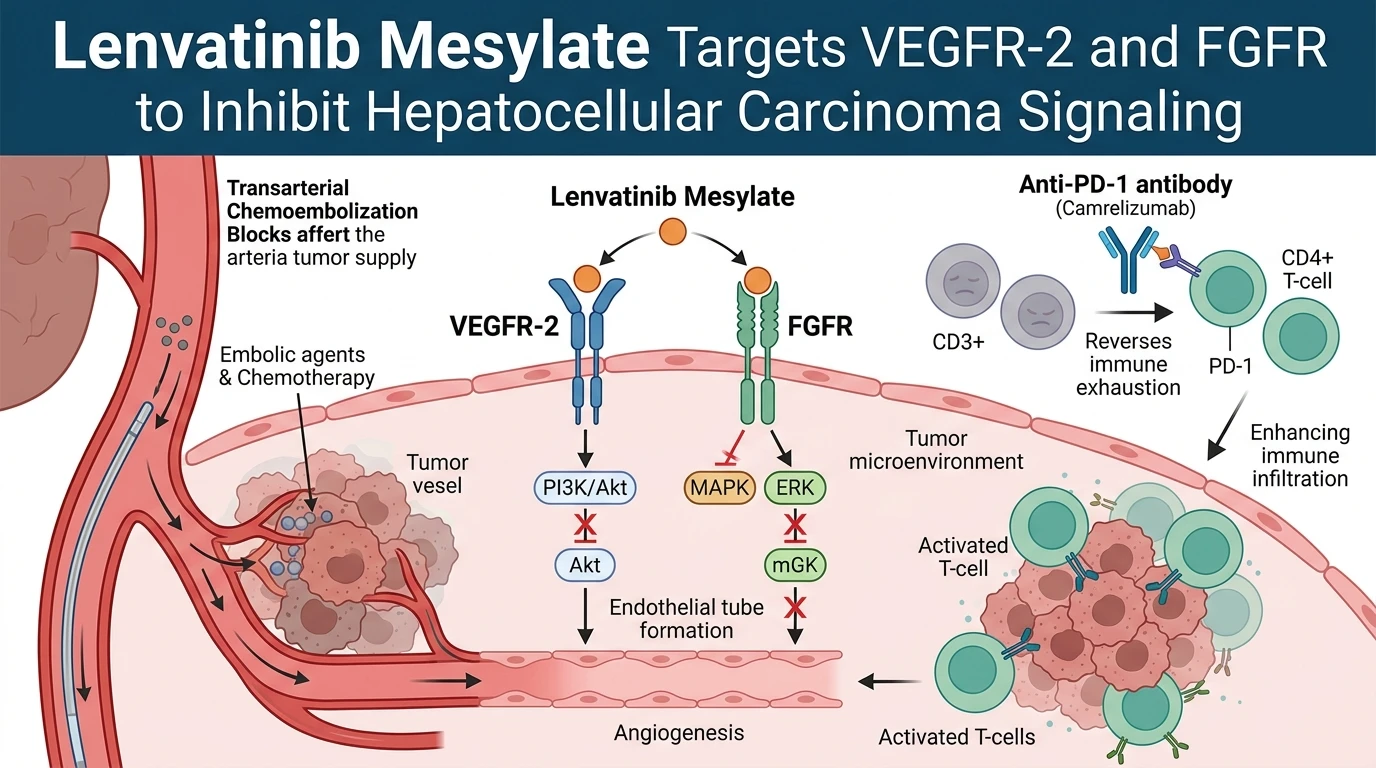
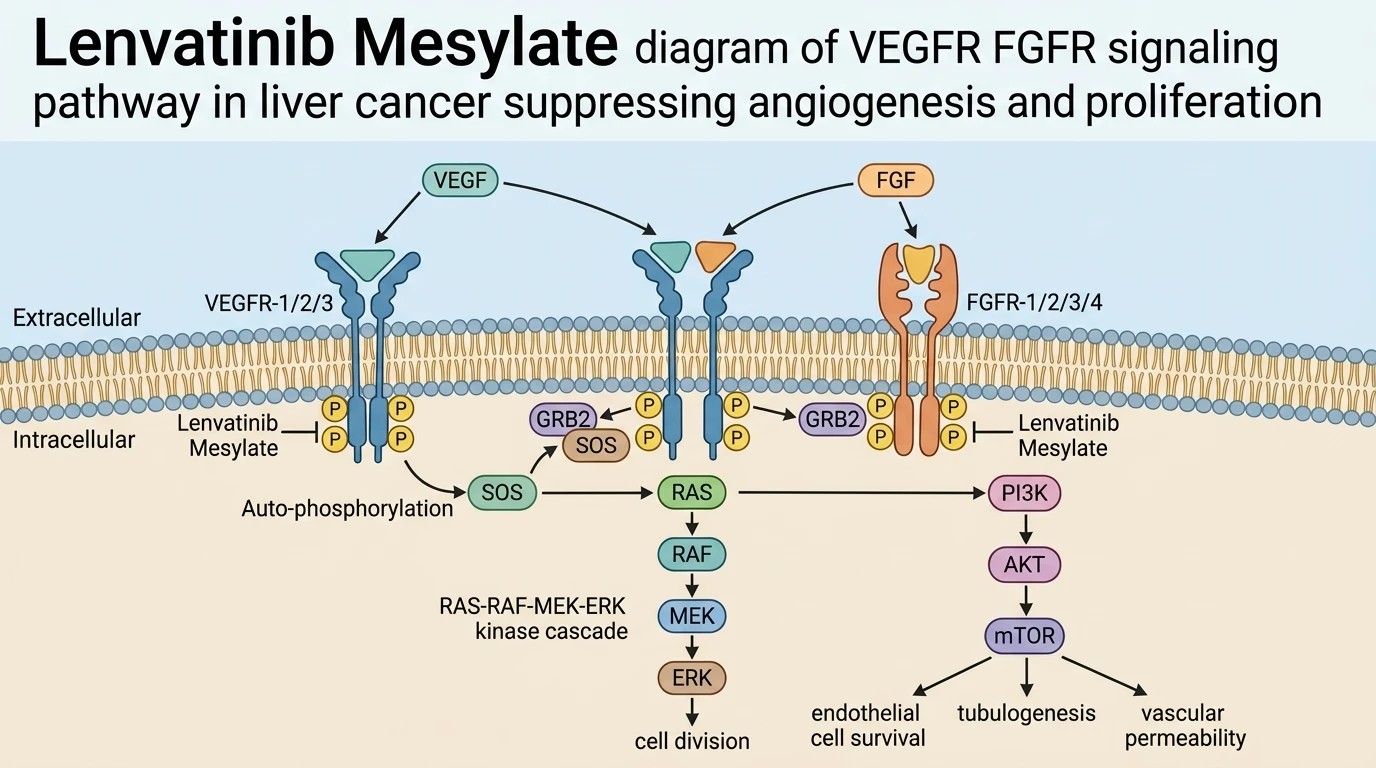
Vascular endothelial growth factor receptors (VEGFR-1, VEGFR-2, VEGFR-3) and fibroblast growth factor receptors (FGFR-1, FGFR-2, FGFR-3, FGFR-4) represent primary receptor tyrosine kinase (RTK) families responsible for driving tumor neoangiogenesis, microvascular permeability, and direct tumor cell proliferation in advanced primary liver malignancies. Advanced hepatocellular carcinoma (HCC) routinely exhibits marked dependence on aberrantly activated angiogenic pathways. Within this hypervascular tumor microenvironment, persistent signaling through VEGFR-2 drives endothelial cell survival, capillary tube formation, and vessel branching, while parallel activation of FGFR isoforms facilitates primary resistance mechanisms to vascular-targeted monotherapies. Lenvatinib Mesylate functions as an orally bioavailable, multi-kinase inhibitor that competitively occupies the ATP-binding site of VEGFR and FGFR tyrosine kinase domains. By blocking receptor transphosphorylation, Lenvatinib Mesylate shuts down downstream signal propagation through the RAF-MEK-ERK and PI3K-AKT pathways, disrupting tumor microvascular networks and suppressing direct oncogenic growth.
In advanced clinical settings, montherapeutic RTK inhibition often encounters adaptive resistance mediated by compensatory signaling networks and immunosuppressive microenvironments. To evaluate enhanced therapeutic strategies, a clinical study evaluated 120 patients diagnosed with advanced primary liver cancer, comparing conventional transarterial chemoembolization (TACE) alone against TACE combined with Lenvatinib Mesylate and the programmed cell death protein 1 (PD-1) inhibitor camrelizumab. TACE induces localized tumor ischemia and necrosis through targeted embolization and cytotoxic chemotherapy delivery. However, embolic hypoxia upregulates systemic angiogenic factors, including VEGF and FGF, which stimulates rapid vascular regeneration and disease relapse. Combining local TACE with systemic VEGFR and FGFR blockade directly neutralizes this hypoxia-induced angiogenic surge. Concurrent administration of camrelizumab prevents PD-L1/PD-1 mediated T-cell exhaustion, forming a rational multi-modal platform that addresses physical tumor burden, vascular supply, and immune evasion simultaneously.
Quantitative clinical evaluation revealed substantial superiority of the triple-combination regimen. Patients receiving TACE plus Lenvatinib Mesylate and camrelizumab achieved an overall response rate (ORR) of 80%, compared to 62% in the TACE monotherapy cohort (p=0.03). This objective response improvement correlated with sharp reductions in circulating serum tumor markers and angiogenic ligands. Post-treatment serum measurements demonstrated marked decreases in alpha-fetoprotein (AFP) and carcinoembryonic antigen (CEA), reflecting reduced viable tumor volume. Parallel reductions in serum VEGF and FGF concentrations confirmed robust systemic target engagement and effective suppression of angiogenic drivers.
Beyond direct vascular and tumor suppression, the combination therapy reconfigured peripheral cellular immune parameters. Patients in the triple therapy arm exhibited significant increases in circulating CD3+, CD4+, and the CD4+/CD8+ T-cell ratio relative to baseline and control measurements. Multi-kinase inhibition by Lenvatinib Mesylate normalizes tumor vasculature, reducing intratumoral hypoxia and facilitating increased infiltration of cytotoxic and helper T lymphocytes. Concurrently, camrelizumab preserves functional T-cell activation within the tumor microenvironment. This immune reconfiguration translated into measured improvements in patient-reported quality of life scores. Safety profiles remained acceptable; the overall incidence of adverse reactions showed no statistical difference between the combination group and the TACE monotherapy group (28% vs 25%, p=0.68). These findings demonstrate that combining TACE with Lenvatinib Mesylate and PD-1 blockade yields pronounced clinical efficacy without compromising patient safety.
At the molecular level, Lenvatinib Mesylate binds to the kinase domain of VEGFR-2 and FGFR isoforms in a distinct binding mode that traps the kinase domain in an inactive conformation. Quantitative binding affinity assays confirm low-nanomolar inhibitory constants against VEGFR-1, VEGFR-2, VEGFR-3, FGFR-1, FGFR-2, FGFR-3, and FGFR-4, alongside platelet-derived growth factor receptor alpha (PDGFR-alpha), RET, and KIT RTKs. This broad inhibition profile prevents the activation of downstream kinase cascades. Phosphorylation of ERK1/2 and AKT is rapidly attenuated following drug exposure, leading to endothelial cell apoptosis and cell cycle arrest at the G1/S phase transition.
Pharmacological Evaluation of Tri-Modal Hepatic Cancer Therapy
Copy code to add this image to your page
Lenvatinib Mesylate is a multi-kinase inhibitor targeting VEGFR-1/2/3 and FGFR-1/2/3/4 ATP-binding pockets. By blocking receptor transphosphorylation, it halts downstream RAF-MEK-ERK and PI3K-AKT cascades, suppressing angiogenesis and tumor cell proliferation. Combining Lenvatinib Mesylate with TACE and camrelizumab overcomes hypoxia-driven angiogenic rebound and restores cellular immune function in advanced primary liver cancer.
Reduction of Circulating Angiogenic and Oncogenic Biomarkers
Circulating biomarker kinetics provided direct evidence of target suppression in patient serum. Serum levels of vascular endothelial growth factor and fibroblast growth factor dropped rapidly following administration of TACE with Lenvatinib Mesylate and camrelizumab. Alpha-fetoprotein levels decreased concurrently. Carcinoembryonic antigen concentrations mirrored this decline. In contrast, TACE monotherapy yielded transient biomarker suppression followed by rebound kinetics. Hypoxia induced by embolization drives reactive VEGF expression. Sustained inhibition of VEGFR-2 and FGFR by Lenvatinib Mesylate effectively neutralized this compensatory response; tumor microvascular density declined rapidly.
Enhancement of CD3+ and CD4+ T-Cell Phenotypes
Flow cytometric analysis of peripheral blood mononuclear cells revealed immunomodulatory changes during combination treatment. Total CD3+ T-lymphocyte populations expanded significantly in the combination arm. CD4+ helper T-cell counts increased in parallel. Consequently, the CD4+/CD8+ ratio shifted toward an immunocompetent profile; baseline immune suppression was substantially mitigated. Normalization of tumor vasculature by Lenvatinib Mesylate reduces interstitial fluid pressure and intratumoral hypoxia. Improved vascular perfusion facilitates immune cell trafficking into the lesion. Simultaneous PD-1 receptor blockade by camrelizumab prevents effector T-cell exhaustion, sustaining systemic and localized anti-tumor immunity.
Safety Profile and Tolerability in Advanced Disease
Adverse event tracking confirmed that tri-modal intervention did not exacerbate overall treatment toxicity. The incidence of adverse reactions was 28% in the combination group compared with 25% in the control group (p=0.68). Common toxicities included manageable hypertension, transient elevation of liver enzymes, and fatigue. No unexpected safety signals emerged during the observation period. Quality of life assessments demonstrated superior patient-reported functional scores in the combination arm. Effective local tumor control combined with systemic target suppression maintained liver function reserve while mitigating cancer-related symptoms.