Linifanib (ABT-869) Multi-Targeted VEGFR PDGFR Kinase Inhibition in Solid Tumor Angiogenesis
Copy code to add this image to your page
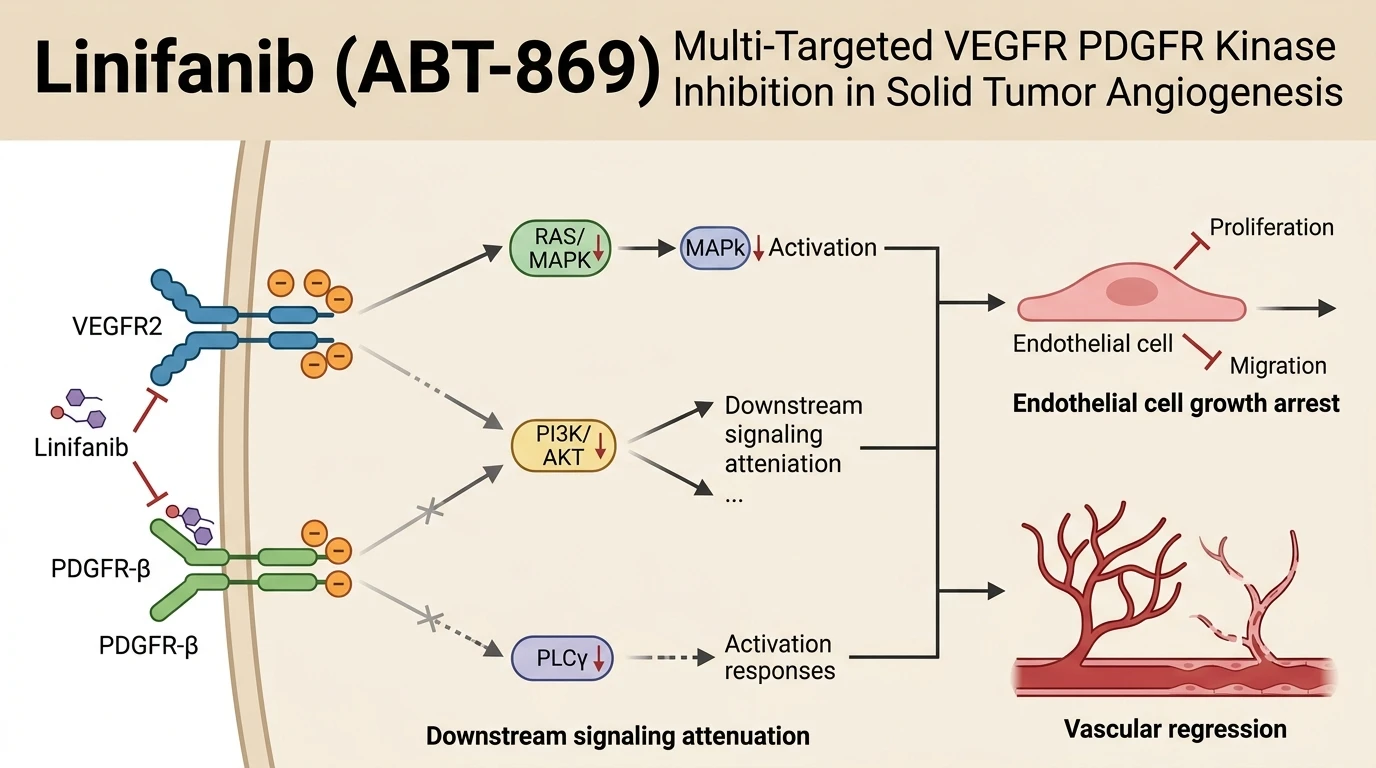
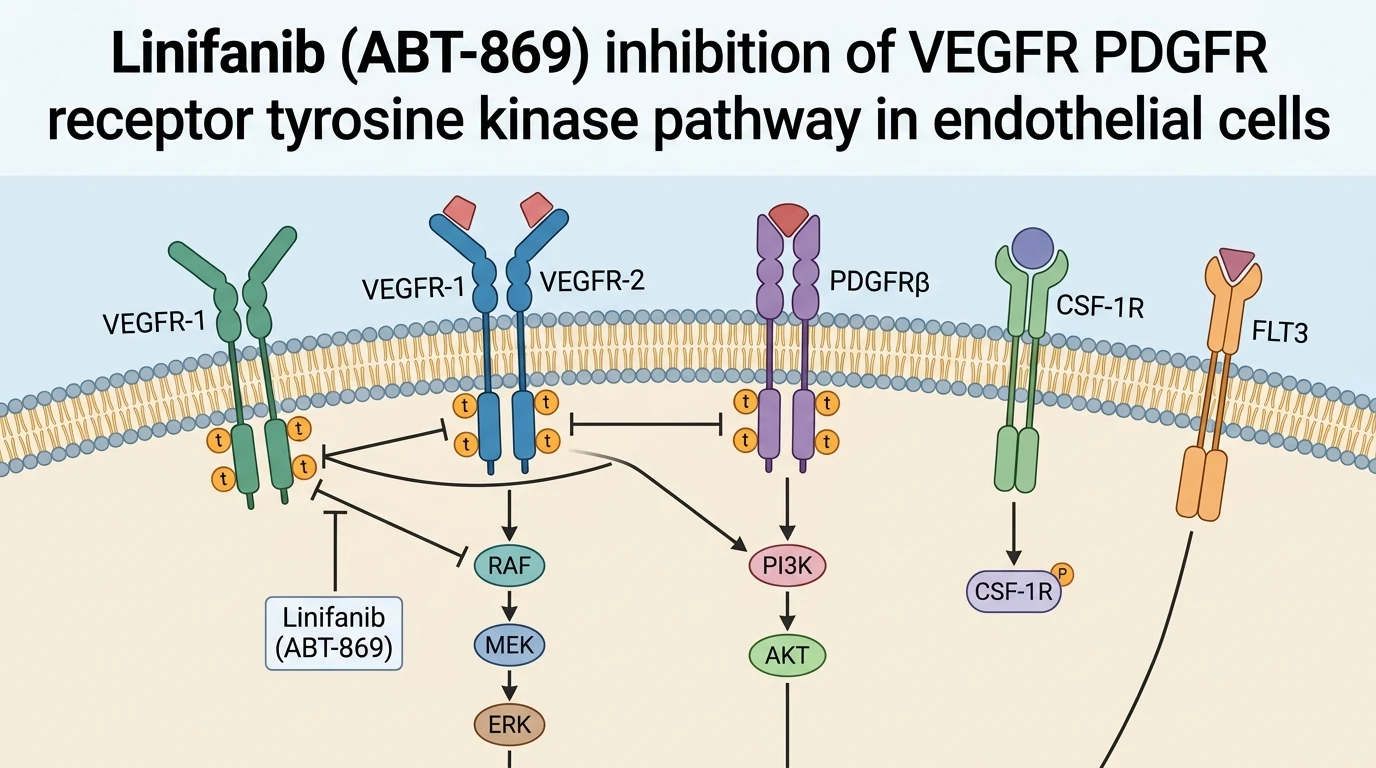
Targeting tumor angiogenesis through multi-receptor tyrosine kinase blockade represents an established pharmacological approach in solid oncology. Receptors such as vascular endothelial growth factor receptors (VEGFR-1 and VEGFR-2) and platelet-derived growth factor receptor-beta (PDGFRβ) drive critical endothelial cell survival, vessel sprouting, and mural cell coverage. Additional receptor tyrosine kinases, including colony-stimulating factor 1 receptor (CSF-1R) and Fms-like tyrosine kinase 3 (FLT3), govern tumor-associated macrophage recruitment and hematopoietic progenitor proliferation. Linifanib (ABT-869) was engineered as a potent, ATP-competitive inhibitor designed to simultaneously block these distinct signaling hubs. By engaging the intracellular catalytic domain of these receptors, the molecule prevents autophosphorylation and abolishes signal transmission through downstream MAPK/ERK and PI3K/AKT cascades.
In biochemical kinase assays, Linifanib (ABT-869) demonstrates low nanomolar IC50 values against VEGFR-1, VEGFR-2, PDGFRβ, CSF-1R, and FLT3, while exhibiting marked selectivity over non-targeted kinases such as EGFR, InsR, and Src family members. Detailed structural characterization of the multitargeted receptor tyrosine kinase inhibitor profile reveals an ATP-competitive mechanism that traps the kinase domain in an inactive conformation. In cellular contexts, this inhibition suppresses ligand-induced receptor phosphorylation, preventing endothelial cell proliferation, migration, and capillary tube assembly in vitro. The ATP-competitive engagement at the ATP-binding pocket of VEGFR-2 impairs downstream activation of phospholipase C gamma (PLCγ) and protein kinase C (PKC). This disrupts endothelial cell survival signaling. Concurrently, inhibition of PDGFRβ prevents pericyte recruitment and destabilizes established tumor microvasculature, exposing endothelial cells to pro-apoptotic stimuli.
The translation of these pharmacological properties was evaluated in a Phase 1 clinical trial involving Japanese patients with advanced, treatment-refractory solid tumors. Patients received daily oral administration of the compound at doses ranging from 0.05 to 0.25 mg/kg. Trial protocol design mandated a standard dose-escalation scheme to define safety, tolerability, pharmacokinetic characteristics, and preliminary clinical efficacy. Patient enrollment encompassed diverse solid tumor histologies, including refractory gastrointestinal, non-small cell lung, and renal cell carcinoma populations. Safety monitoring included routine hematologic, hepatic, renal, and cardiac monitoring protocols.
Pharmacokinetic evaluations demonstrated rapid oral absorption, with peak plasma concentrations reached within several hours post-dose. Systemic exposure scaled dose-proportionally between 0.10 and 0.25 mg/kg daily dosing regimens. Minimal intra-patient variability and predictable drug accumulation were observed upon repeat daily dosing. Renal clearance accounted for a minor fraction of overall elimination, indicating predominant hepatic metabolism. Elimination half-life values supported once-daily administration, maintaining plasma concentrations above target inhibitory thresholds across the 24-hour interval.
Pharmacodynamic monitoring provided direct evidence of target suppression within patient systemic circulation. Plasma concentrations of placental growth factor (PlGF) exhibited dose-dependent increases following treatment initiation. PlGF upregulation serves as a recognized surrogate biomarker for systemic VEGFR inhibition, resulting from target neutralization and ligand displacement. Corresponding decreases in soluble VEGFR-2 levels provided dual biomarker verification of pathway inhibition. Clinical safety observations indicated a manageable safety profile consistent with antiangiogenic class effects. Observed dose-limiting toxicities at elevated dose levels included Grade 3 alanine aminotransferase (ALT) elevation and Grade 1 T-wave inversion on electrocardiographic tracking. The most frequent treatment-emergent adverse events were hypertension, cutaneous rash, neutropenia, and proteinuria.
Antitumor activity was observed across the patient cohort. Two patients achieved confirmed partial responses, representing an overall objective response rate of 11.1%. An additional twelve patients achieved disease stabilization. Notably, four patients sustained disease control beyond 48 weeks of continuous daily administration. These clinical findings validate the antiangiogenic mechanism and therapeutic utility of target suppression in advanced solid malignancies.
Phase 1 Clinical Pharmacokinetics and Biomarker Evaluation
Copy code to add this image to your page
Linifanib (ABT-869) acts as an ATP-competitive, multi-targeted receptor tyrosine kinase inhibitor blocking VEGFR-1, VEGFR-2, PDGFRβ, CSF-1R, and FLT3. By inhibiting autophosphorylation of these receptors, the agent impairs downstream MAPK/ERK and PI3K/AKT signaling cascades. This kinase blockade disrupts endothelial cell proliferation, tube formation, microvascular survival, and pericyte recruitment, resulting in inhibition of tumor-induced angiogenesis and tumor growth suppression in solid malignancies.
Dose-Proportional Exposure and Biomarker Modulation in Patients
Daily oral administration of Linifanib across the dose range of 0.10 to 0.25 mg/kg yielded dose-proportional pharmacokinetic parameters. Maximum plasma concentration and area under the plasma concentration-time curve increased linearly with dose. Plasma concentrations remained above target inhibition thresholds throughout the daily dosing interval. Target engagement was confirmed by dose-dependent elevations in circulating placental growth factor (PlGF). PlGF levels rose significantly following drug exposure. This biomarker induction reflects systemic neutralization of VEGFR-1 and VEGFR-2 signaling cascades.
Manageable Toxicity Profile and Sustained Clinical Disease Control
In eighteen Japanese patients with refractory solid tumors, dose-limiting toxicities included Grade 3 alanine aminotransferase elevation and Grade 1 T-wave inversion. Frequently observed adverse events comprised hypertension, cutaneous rash, neutropenia, and proteinuria. These toxicities were medically manageable through standard supportive interventions or temporary dose modification. Clinical activity was observed across multiple solid tumor types. Confirmed partial responses occurred in two patients (11.1%). Stable disease was achieved in twelve patients, with four maintaining disease stabilization past 48 weeks of continuous therapy.