Cediranib (AZD2171) Pan-VEGFR Kinase Inhibition in Newly Diagnosed Glioblastoma Therapeutics
Copy code to add this image to your page
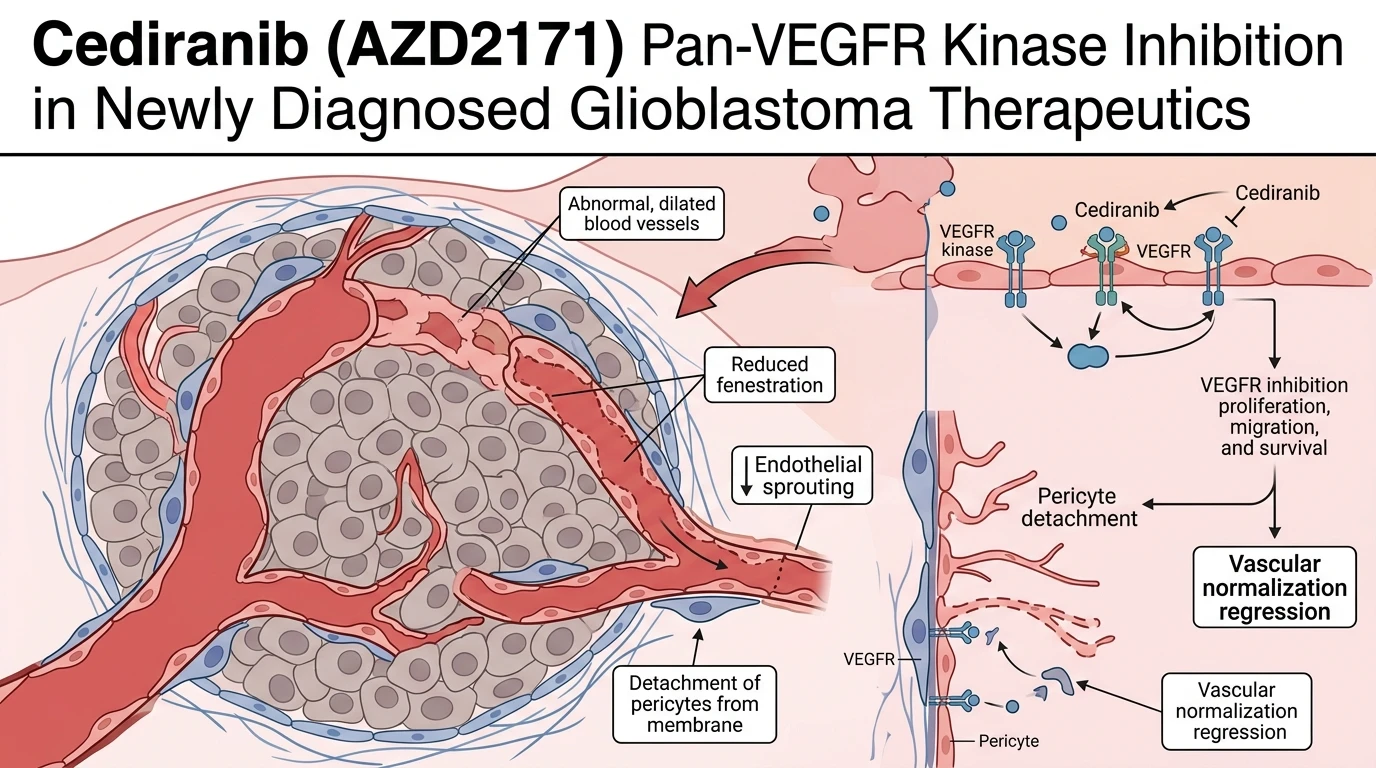
Targeting tumor angiogenesis through vascular endothelial growth factor receptor (VEGFR) axis blockade remains a central strategy in high-grade glioma research. Cediranib (AZD2171) is a potent, oral pan-VEGFR tyrosine kinase inhibitor designed to block ATP-binding pockets across VEGFR-1, VEGFR-2, and VEGFR-3, while exhibiting secondary activity against c-Kit and platelet-derived growth factor receptor-beta (PDGFRβ). Quantitative biochemical assays demonstrate nanomolar enzymatic inhibition against VEGFR-2 ($IC_{50} < 1\text{ nM}$), effectively disrupting endothelial cell proliferation, migration, and capillary tube assembly. Available VEGFR-2 kinase domain structural models show how competitive small-molecule inhibitors stabilize the inactive catalytic conformation, blocking trans-autophosphorylation of intracellular tyrosine residues.
Glioblastoma multiforme features pronounced microvascular proliferation driven by severe tumor hypoxia and elevated local concentrations of VEGF. Standard-of-care management relies on surgical resection followed by concurrent radiation and temozolomide chemotherapy. Despite aggressive multimodal interventions, local recurrence occurs universally. Vascular normalization—the transient structural and functional restructuring of abnormal tumor vessels—presents a dual therapeutic paradigm. Reversible reduction in vessel diameter and permeability reduces peritumoral edema; however, persistent blockade restricts oxygenation, triggering hypoxia-driven invasive cellular phenotypes.
To rigorously test whether pan-VEGFR kinase blockade improves outcomes in upfront glioblastoma, the randomized, phase II, double-blind NRG/RTOG 0837 trial evaluated the addition of oral AZD2171 to standard radiation and temozolomide versus placebo in newly diagnosed patient cohorts. Primary clinical endpoints focused on evaluating progression-free survival (PFS) alongside safety metrics and overall survival (OS).
The empirical outcomes of the NRG/RTOG 0837 study confirmed a statistically significant improvement in short-term disease control. Patients receiving cediranib achieved a 6-month PFS rate of 46.6%, compared to 24.5% in the control cohort ($P = .005$). Median PFS lengthened from 2.7 months in the placebo arm to 6.2 months in the experimental arm, yielding a hazard ratio of 0.67 ($P = .03$). Radiographic assessments demonstrated early reductions in fluid-attenuated inversion recovery (FLAIR) signals and contrast enhancement, consistent with reduced microvascular permeability.
Despite distinct PFS prolongation, the trial failed to translate early radiographic stabilization into a statistically meaningful overall survival advantage. Median OS was recorded at 14.5 months for the experimental arm versus 13.8 months for placebo ($HR = 0.87, P = .44$). This therapeutic decoupling mirrors observations documented across trials evaluating anti-VEGF monoclonal antibodies in high-grade gliomas.
Safety evaluations revealed heightened systemic toxicities in the experimental cohort. Grade 3 or higher adverse events occurred in 83.7% of patients receiving the active kinase inhibitor, compared to 67.3% in the placebo group ($P = .02$). Dominant toxicities included severe hypertension, fatigue, diarrhea, and hematologic toxicities, requiring dose interruptions or step-down modifications. These adverse reactions constrained continuous drug delivery, potentially counteracting localized antitumor pressure.
Mechanistically, the dissociation between PFS and OS reflects persistent challenges in anti-angiogenic glioblastoma therapy. Pharmacological suppression of VEGFR-2 and PDGFRβ temporarily corrects vascular leaks, attenuating cerebral edema and prolonging time to radiographic progression. However, persistent vascular deprivation induces severe intra-tumoral hypoxia. Hypoxic signaling upregulates alternative pro-angiogenic factors, prompting glioblastoma cells to transition toward co-option of pre-existing parenchymal vessels and diffuse single-cell infiltration into surrounding brain tissue. Consequently, while initial microvascular collapse extends progression-free metrics, it fails to eliminate non-angiogenic tumor subpopulations.
Clinical Evaluation and Pharmacodynamic Outcomes in Glioblastoma
Copy code to add this image to your page
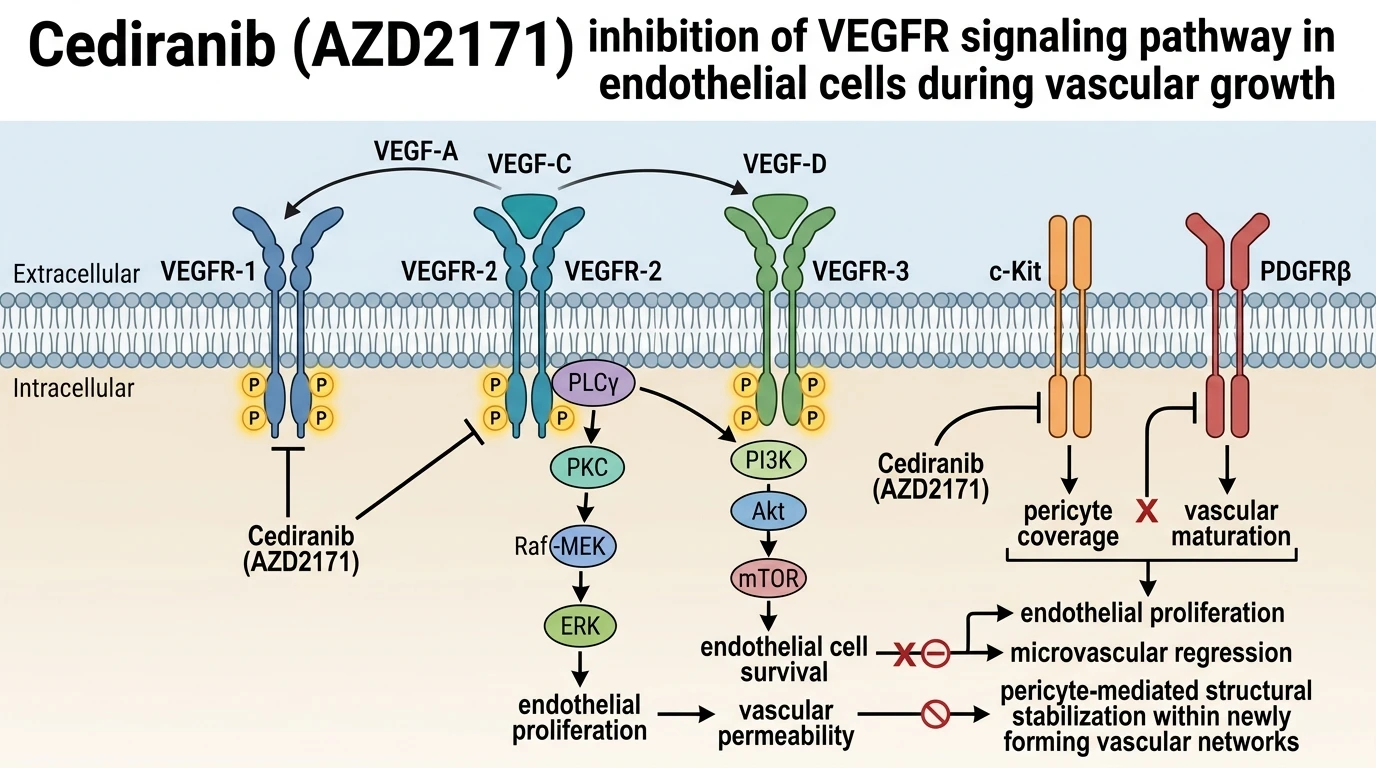
Cediranib (AZD2171) functions as an oral pan-VEGFR tyrosine kinase inhibitor targeting VEGFR-1, VEGFR-2, and VEGFR-3, with additional inhibitory activity against c-Kit and PDGFRβ. By competing for intracellular ATP-binding domains, it prevents trans-autophosphorylation and downstream signaling through the PLCγ-ERK and PI3K-Akt pathways. This enzymatic blockade disrupts endothelial proliferation, capillary sprouting, and pericyte-mediated vessel stabilization. In glioblastoma, these pharmacological actions induce vascular normalization and transiently arrest tumor angiogenesis, extending progression-free survival without conferring a long-term overall survival advantage.
Progression-Free Survival Prolongation in NRG/RTOG 0837 Cohorts
Administering AZD2171 alongside chemoradiation generated measurable improvements in early disease control. 6-month progression-free survival reached 46.6% in the experimental arm versus 24.5% under placebo conditions ($P = .005$). Median PFS increased to 6.2 months relative to 2.7 months in control groups. Structural imaging revealed rapid reductions in contrast enhancement within weeks of initiating therapy. Vessel normalization decreased interstitial fluid pressure. Microvascular regression halted local edema formation. However, these physiological adjustments reflect vascular altered permeability rather than cytocidal destruction of malignant stem-like populations.
Overall Survival Uncoupling and Grade Three Adverse Event Rates
Despite radiographic improvements, median overall survival showed no significant divergence between treatment arms. Patients receiving AZD2171 achieved a median OS of 14.5 months compared to 13.8 months in placebo controls ($HR = 0.87, P = .44$). Severe systemic toxicities limited continuous dosing regimens. Grade 3 or higher adverse events rose to 83.7% in the intervention cohort ($P = .02$). Common toxicities included uncontrolled hypertension, fatigue, and gastrointestinal distress. Uncoupling of PFS from OS highlights metabolic adaptation mechanisms. Hypoxia-driven upregulation of alternative pro-invasive pathways enables cellular survival despite persistent vascular blockade.