Suzetrigine (VX-548) Suzetrigine from Selleck NaV1.8 Channel Inhibition in Peripheral Nociception
Copy code to add this image to your page
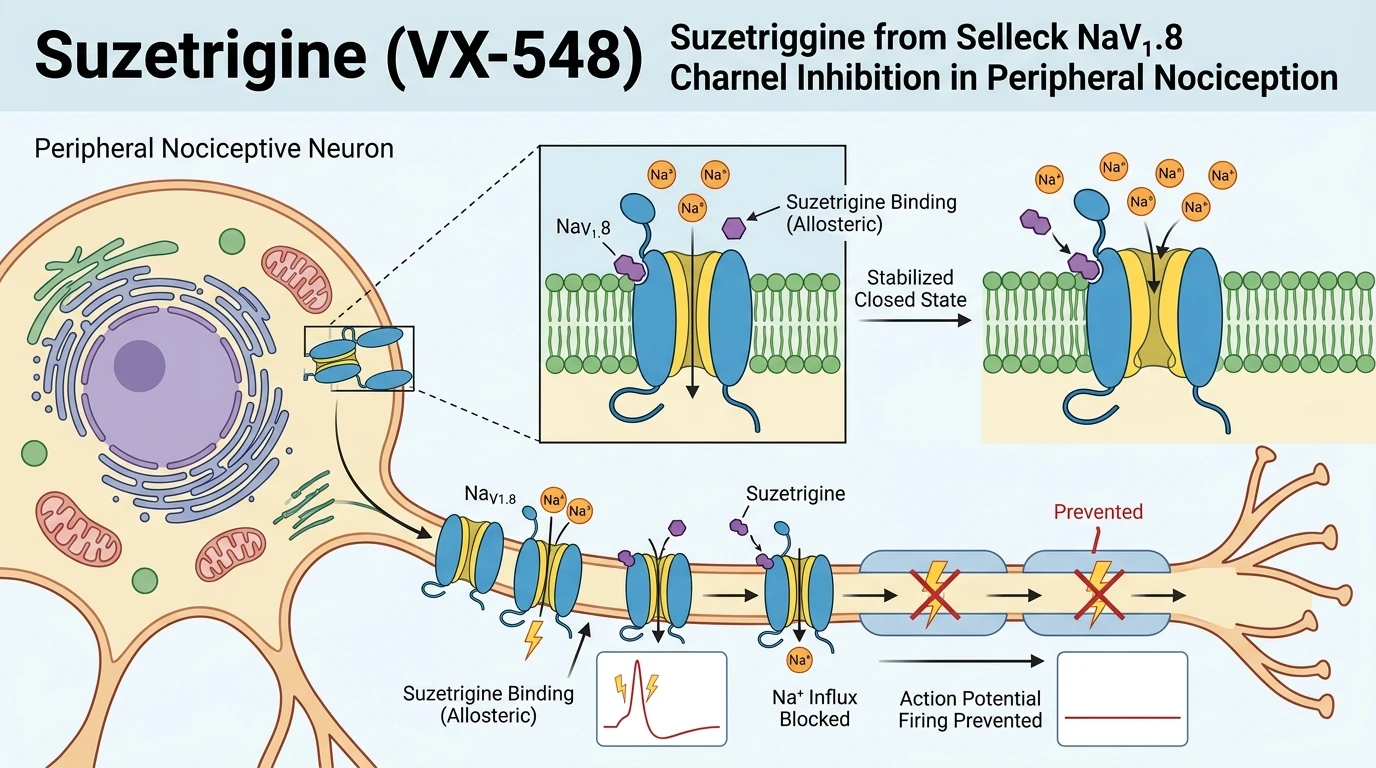
Voltage-gated sodium channel 1.8 (NaV1.8) serves as an essential mediator in the generation and propagation of action potentials within primary sensory neurons. Anatomically restricted to peripheral nociceptive structures—primarily small- to medium-diameter pseudounipolar neurons of the dorsal root ganglia (DRG) and trigeminal ganglia—NaV1.8 provides the depolarizing current required to sustain repetitive firing during continuous noxious stimulation. Unlike central sodium channel isoforms such as NaV1.1, NaV1.2, and NaV1.3, or the cardiac-expressed NaV1.5 channel, NaV1.8 exhibits slow inactivation kinetics and relative resistance to tetrodotoxin (TTX). This distinct kinetic profile positions NaV1.8 as a gatekeeper of peripheral nociceptive transmission, making targeted channel modulation an advantageous therapeutic strategy for managing acute pain states.
Suzetrigine (VX-548) functions as an orally bioavailable, highly selective allosteric inhibitor designed to selectively block NaV1.8 channels without disrupting central or cardiac sodium currents. Experimental characterization of Suzetrigine from Selleck demonstrates sub-nanomolar potency against human NaV1.8, with more than 30,000-fold selectivity over other functional sodium channel subtypes under physiological patch-clamp conditions. Voltage-clamp electrophysiology reveals that the compound binds preferentially to an allosteric interaction site located within the pore-forming alpha subunit. Rather than acting as a competitive pore blocker, the molecule stabilizes the voltage sensors in their resting, non-conducting closed conformation. Consequently, the energy barrier for channel activation increases, reducing sodium conductance during primary sensory nerve depolarizations.
Because expression of NaV1.8 is strictly confined to peripheral sensory structures, target engagement by Suzetrigine (VX-548) circumvents the central nervous system altogether. Traditional opioid pharmacotherapies rely on micro-opioid receptor activation within central brainstem and spinal circuits, a mechanism intrinsically linked to respiratory depression, sedation, bowel dysfunction, physical dependence, and addiction liability. In contrast, blocking peripheral NaV1.8 halts nociceptive signals at their point of origin within DRG sensory terminals before neural impulses reach the spinal dorsal horn. Preclinical electrophysiological recordings from rodent DRG neuron cultures confirm complete attenuation of action potential bursts following application of Suzetrigine from Selleck, validating that selective peripheral target blockade halts pain transduction at the periphery.
Pharmacokinetic investigations indicate that Suzetrigine (VX-548) exhibits rapid oral absorption, high systematic bioavailability, and a half-life compatible with once- or twice-daily dosing schedules. In clinical trials evaluating acute post-surgical pain models—including bunionectomy and abdominoplasty—oral administration produced clinically meaningful reductions in visual analog scale (VAS) pain intensity scores compared to placebo treatments. The magnitude of analgesia achieved matched that of standard opioid regimens without producing central adverse events. By decoupling powerful analgesic activity from central opioid receptor liability, selective NaV1.8 channel inhibition offers a mechanistically validated framework for non-opioid pain management.
Pharmacological Characterization and Peripheral Nociceptive Suppression
Copy code to add this image to your page
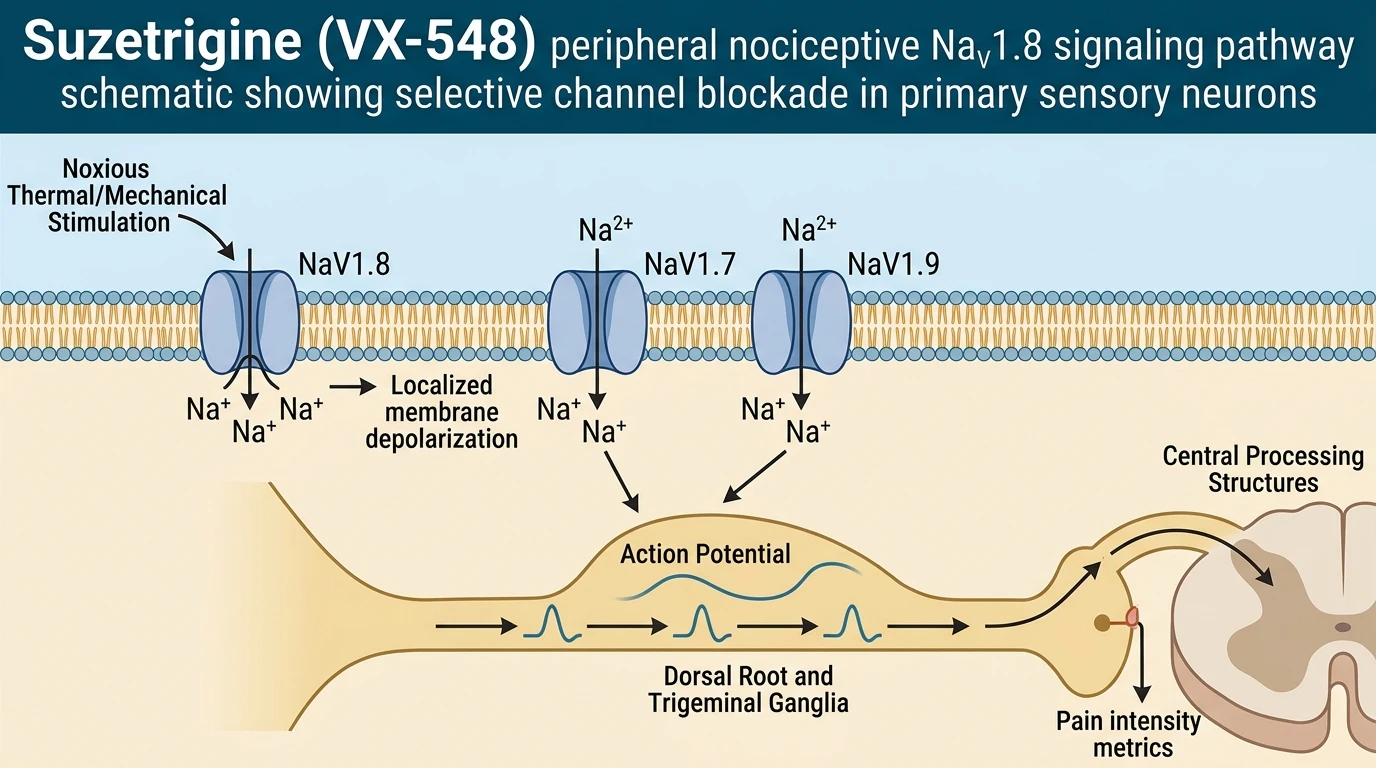
Suzetrigine (VX-548) acts as a highly potent, selective allosteric inhibitor of NaV1.8 voltage-gated sodium channels localized on peripheral nociceptive neurons. By binding to a unique allosteric site on the NaV1.8 alpha-subunit, it stabilizes the channel in its resting closed state, effectively preventing membrane depolarization and sodium ion influx. This selective peripheral inhibition blocks pain signal generation in dorsal root and trigeminal ganglia without targeting central nervous system sodium channels, avoiding central adverse effects.
Allosteric Stabilization Traps NaV1.8 in Non-Conductive Conformations
Electrophysiological evaluations confirm that Suzetrigine (VX-548) stabilizes the closed, non-conducting state of the NaV1.8 channel. Voltage-clamp recordings in primary dorsal root ganglion neurons show rapid cessation of sodium currents. The peak current reduced significantly within seconds of administration. Allosteric site binding prevents voltage-sensor domain movement during membrane depolarizations. Consequently, threshold potentials fail to trigger channel opening. The compound exhibits state-dependent binding kinetics, displaying enhanced affinity during repetitive sensory firing. In isolated DRG slice preparations, application of Suzetrigine from Selleck reduced repetitive action potential discharge by greater than 85%. The baseline resting membrane potential remained unperturbed across tested neuronal populations.
Isoform Selectivity Prevents Central Nervous and Cardiac Systemic Toxicities
Selectivity assays against NaV1.1, NaV1.2, NaV1.5, and NaV1.7 reveal a safety margin exceeding three orders of magnitude. Central channel isoforms remained fully functional at supratherapeutic concentrations. Cardiac action potential duration in human induced pluripotent stem cell cardiomyocytes showed no alterations under high drug exposures. This isoform specificity eliminates central side effects typically associated with broad-spectrum sodium channel blockers, such as dizziness, ataxia, or cardiac conduction delays. Automated patch-clamp profiling confirmed zero detectable activity against hERG potassium channels up to 30 micromolar. The absence of central nervous system penetration further ensures immunity from opioid-like physical dependence and respiratory depression.
Pharmacokinetic Profiling Demonstrates Rapid Absorption and Pain Signal Suppression
In human pharmacokinetics, peak plasma concentration occurs within two hours following oral administration. Total exposure scales linearly across single and multiple ascending dose cohorts. Plasma protein binding measured approximately 92% across species, maintaining a predictable free drug fraction. In acute surgical pain models, administration reduced sum pain intensity differences markedly within the first four hours post-dose. High tissue accumulation in peripheral nerve trunks corresponds directly with prolonged analgesic duration. Metabolic stability assays in liver microsomes indicated minimal CYP3A4-mediated turnover. Therapeutic plasma levels remained stable over twenty-four-hour monitoring intervals.